42 Tomorrow Never Comes
Apathy, Abulia, and the Failure to Initiate
42.1 A represented future does not initiate itself
Chapter 41 brought us to the difference between an available possibility and an initiated course of action. Knowing another route to water is useful only if that knowledge can influence what the animal does when water matters. The final question of this unit concerns that influence: how does a potentially valuable goal recruit a body into action?
A person may know that a bill must be paid, explain what will happen if it is ignored, and possess the money and motor capacity needed to pay it. The envelope can remain unopened. A patient may agree that walking would preserve strength, describe the route down the corridor, and stand when asked. Left alone, the patient does not rise. These are illustrative situations, not diagnostic tests. They direct attention to a possibility the clinical evidence can examine: knowledge and capacity may remain available while their influence on spontaneous behavior is greatly reduced.
This gap is often hidden by the word motivation. We say that someone wanted an outcome enough to act or did not want it enough to begin. The word compresses several problems. How much does the expected outcome matter in the current bodily and social state? What effort, delay, uncertainty, and risk will the organism accept? Which action gains priority? What supports starting, continuing, and resuming after an interruption? These questions distinguish contributions to one ongoing process. They do not specify stages that must finish in order.
The syndromes in this chapter separate some of those operations. Apathy reduces goal-directed activity. Abulia produces a more severe loss of initiative and spontaneous behavior. Auto-activation deficit makes thought and action strikingly dependent on external stimulation. Akinetic mutism can leave a person awake but producing almost no spontaneous speech or movement. Their boundaries are not perfectly stable, and different injuries can produce partly different mixtures. Together they establish one central fact:
A represented future does not initiate itself. An available goal must acquire enough control to recruit effort, bodily preparation, action selection, motor release, and persistence.
The chapter’s title comes from an observation made during the era of prefrontal lobotomy. Some operated patients could discuss plans for the next day, yet the plans did not organize what they did. “Tomorrow never comes,” Freeman and Watts wrote [@freemanwatts1939frontal]. The phrase remains clinically revealing if it is treated as a metaphor. Tomorrow may still be available in speech. What fails is its power to reorganize today.
42.2 Apathy, abulia, auto-activation deficit, and akinetic mutism
The broadest term is apathy. A 2018 international consensus group defined it as a quantitative reduction in goal-directed activity relative to the person’s previous functioning. The proposed criteria also require persistence for at least four weeks, involvement of at least two of three dimensions—behavior/cognition, emotion, and social interaction—and significant functional impairment, with specified exclusions [@robertetal2018apathy]. The definition is descriptive: it identifies a clinically consequential change without assuming that every case has the same cause. The persistent syndrome should not be confused with an afternoon of inactivity.
Apathy is not simply laziness, weak character, or a failure to understand what should be done. It is also not identical to anhedonia, the reduced capacity to experience pleasure, although the two can coexist. A person may enjoy an activity after someone else starts it yet rarely initiate it. Another may begin tasks but derive little pleasure from their outcomes. Apathy can accompany depression, but it can also occur without pervasive sadness, guilt, hopelessness, or suicidal thinking. Conversely, the absence of reported sadness does not prove that every other affective or cognitive process is intact [@husainroiser2018apathy].
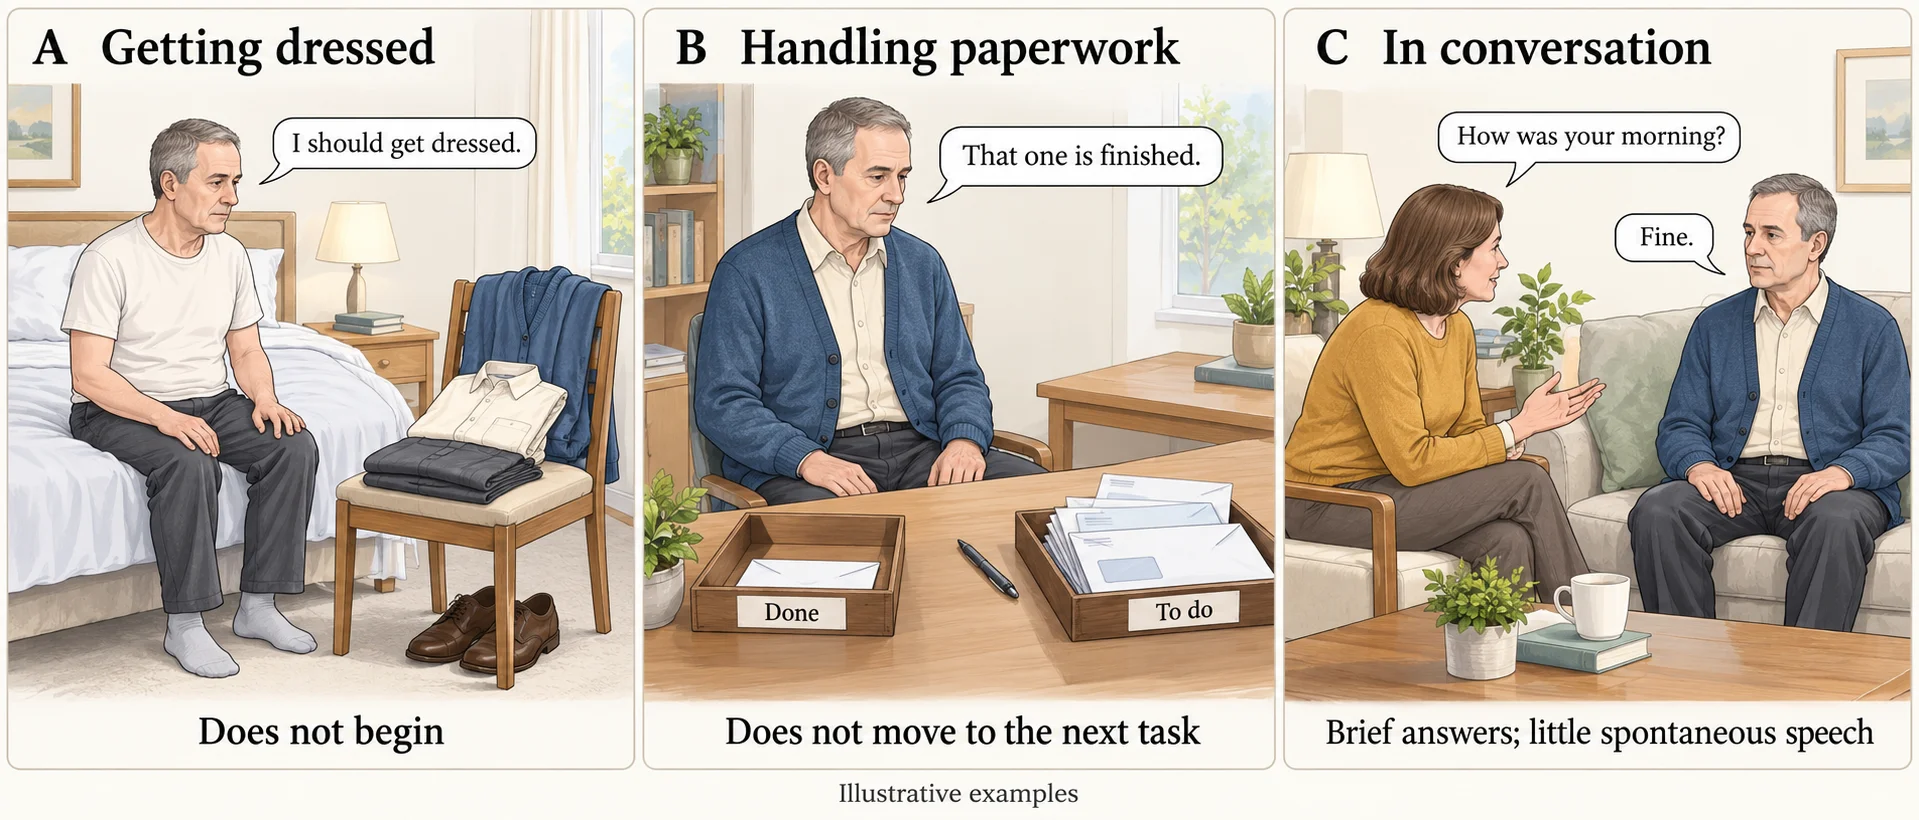
Abulia usually refers to a more marked reduction in initiative. Speech becomes sparse, answers are delayed, and behavior may stop unless another person repeatedly prompts it. Basic movement can remain possible on command. The distinction from severe apathy is one of degree and pattern rather than a universally accepted boundary.
The older term psychic akinesia is most useful when attached to a more specific syndrome now called auto-activation deficit. In the classic cases, spontaneous thought and behavior were profoundly reduced, while sustained external stimulation could produce unexpectedly elaborate speech or action. Some patients described a mental emptiness when nothing in the environment called for a response. The syndrome was first associated with bilateral basal-ganglia lesions and was later reported after frontal and bithalamic injury [@laplaneetal1984psychic; @laplanedubois2001autoactivation].
Akinetic mutism describes an extreme paucity of spontaneous movement and speech in a person who appears awake. Eye opening and visual tracking may remain, and elementary responses can sometimes be elicited. Apparent wakefulness does not establish normal awareness or comprehension. The syndrome can follow bilateral medial frontal injury, but related presentations also occur after subcortical and brainstem injury [@nemethetal1988akinetic; @darbyetal2018volition]. The examination must distinguish deficient initiation from impaired arousal, language, or movement, including mixtures of these problems.
The terms overlap, but they are not interchangeable. One influential framework separates emotional-affective, cognitive, and auto-activation routes to reduced goal-directed behavior, while emphasizing that several can coexist in one person [@levydubois2006apathy].
| Clinical term | Characteristic reduction | What may remain accessible | Main caution |
|---|---|---|---|
| Apathy | Goal-directed activity across behavioral, cognitive, emotional, or social domains | Many capacities may remain, with variable benefit from structure or prompting | A broad syndrome with several possible component failures |
| Abulia | Initiative, spontaneous speech, and self-started action | Wakefulness, comprehension, and movement on command may be relatively preserved | Boundaries with severe apathy and akinetic mutism vary across traditions |
| Auto-activation deficit | Internally generated thought and behavior | Sustained external stimulation can produce a striking temporary restoration | Most closely related to classic psychic akinesia, not a synonym for every abulic state |
| Akinetic mutism | Nearly all spontaneous speech and movement | Eye opening, visual tracking, and occasional commanded action can remain | Apparent wakefulness does not establish intact awareness; assess arousal, comprehension, and motor capacity separately |
The table is not a severity ladder. A patient can be apathetic yet verbally active. Another can be nearly mute because language production is impaired rather than because initiative is lost. Paresis can prevent action after a goal has been selected. Fatigue can make sustained effort physiologically expensive. Catatonia, delirium, severe depression, aphasia, disorders of consciousness, and medication effects can all produce superficial similarities. Clinical interpretation therefore asks what the person can do under carefully varied conditions, not merely how much spontaneous behavior appears at the bedside.
42.3 When external structure restores action
The classic cases of auto-activation deficit make the role of the environment unusually visible. Laplane and colleagues described patients with bilateral basal-ganglia lesions who showed very little spontaneous behavior. They might sit silently, fail to begin ordinary activities, and report little spontaneous mental content. Persistent questioning or direct instruction could nevertheless evoke appropriate answers and organized actions. The underlying capacities had not vanished. They had become difficult to recruit without external structure [@laplaneetal1984psychic; @laplanedubois2001autoactivation].
Benke and colleagues described two patients with left basal-ganglia hemorrhages. One had extensive caudate damage; the other had predominantly putaminal and pallidal damage with relatively minor caudate involvement. Both initially showed abulia together with substantial attentional, executive, and memory impairment [@benkeetal2003caudate]. Their resemblance is informative, but neither the lesion nor the deficit was a selective removal of initiative from an otherwise intact person.
The contrast between spontaneous inactivity and behavior elicited by a cue is often described as preserved reactivity with lost self-activation. It should not be translated into a division between present and future. An external prompt can concern next week: “Begin preparing for your appointment.” A self-generated action can concern the immediate present: reaching for a glass because one is thirsty. The distinction concerns how much of the task’s organization the environment supplies.
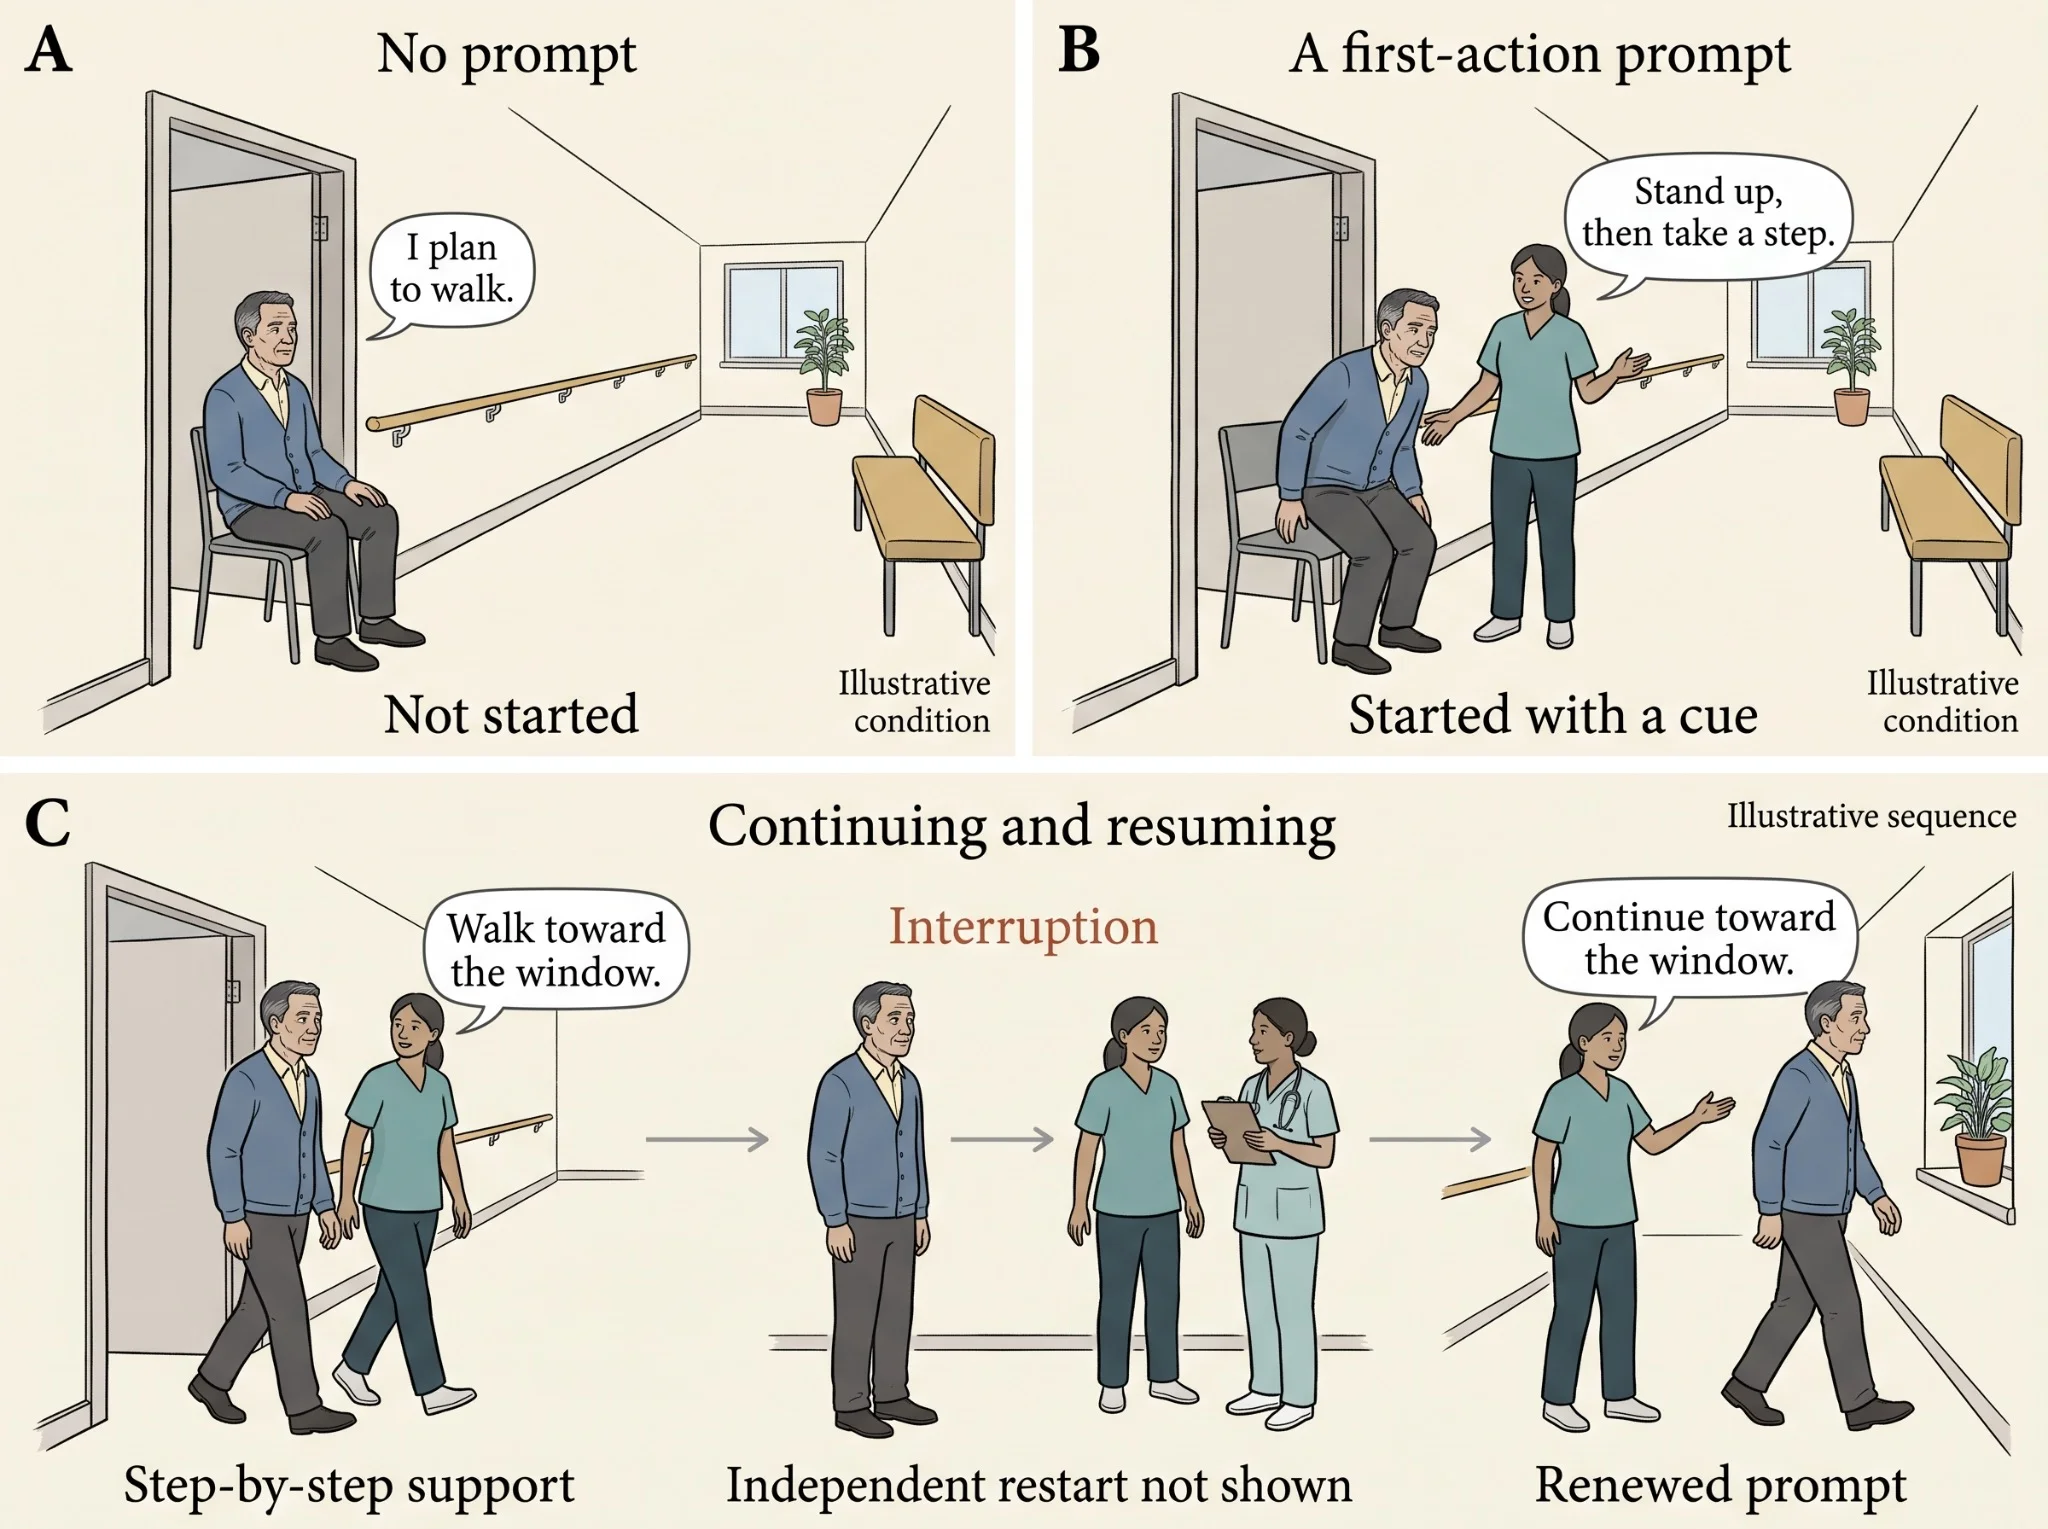
A cue can help in several ways. It can specify the goal, identify a first movement, reduce competition among possible starting actions, increase arousal, divide a task into manageable steps, or re-engage the person after behavior has stopped. These are possible explanations of a cue’s benefit, not mechanisms individually established by the classic case reports. In a schematic dressing example, “Pick up the shirt” supplies a more definite next action than “Get dressed.” The shirt and further prompts can then support subsequent steps. Successful prompted behavior need not mean that a missing desire has been restored.
Experiments with self-initiated and externally triggered movement show why the distinction cannot be assigned to one anatomical switch. Jahanshahi and colleagues measured regional blood flow with PET and electrical movement-related potentials while healthy participants and patients with Parkinson’s disease extended a finger at a self-selected time or in response to a tone. The conditions recruited substantially overlapping motor systems. In healthy participants, right dorsolateral prefrontal activity was the only significant regional difference in the direct comparison. During self-initiated movement, the Parkinson’s group showed reduced early electrical preparation and lower activation in supplementary-motor, anterior-cingulate, putaminal, and related regions [@jahanshahietal1995selfinitiated]. This task separates timing conditions; it is not a model of every everyday initiation failure. External triggering changes the information organizing an action system that remains largely shared.
The clinical response to prompting therefore establishes less—and more—than it first appears to. It does not identify a single self-activation center. It does show that the difference between capacity and access can be enormous. A patient who rarely speaks may still produce a coherent account when sufficiently engaged. A patient who does not begin a routine may still execute its components when the environment supplies a starting point and maintains the sequence.
That distinction matters clinically and conceptually. Sparse spontaneous behavior should not automatically be read as absent comprehension, absent preference, or absent personhood. At the same time, a response obtained under intensive prompting does not prove that cognition is otherwise normal. The prompt has changed the task. It has temporarily supplied organization that everyday life usually requires the person to generate.
As Chapter 38 also showed, an instruction can remain reportable without continuing to organize the next action. Starting a sequence, keeping its goal effective, and resuming it after a pause are related questions that need separate observations.
External structure can make an available capacity behaviorally accessible without revealing exactly which internally generated operation the structure has replaced.
42.4 From expected value to effort, vigor, and initiation
Chapter 37 showed that an outcome’s value depends on bodily state, learned consequences, delay, uncertainty, and alternatives. The present chapter separates that significance from its effectiveness in recruiting action. This refines the broad selection problem already developed in Choosing What to Do, which includes vigor, continuation, termination, and switching as well as beginning. It does not add a separate motivational stage after selection has finished.
One rare case makes reward sensitivity visible. A man developed profound apathy after bilateral lesions predominantly involving the internal globus pallidus (GPi); limited left external-pallidal involvement was also possible. His elementary neurological examination was largely normal. In two eye-movement tasks, reward had unusually little effect on when he made saccades. Levodopa partly restored reward sensitivity, and the dopamine agonist ropinirole produced a larger change alongside improved everyday engagement [@adametal2013dopamine]. The case links pallidal injury, reward-dependent behavior, and pharmacological modulation. It neither localizes the drug’s action to the damaged GPi nor establishes a universal dopamine deficiency in apathy.
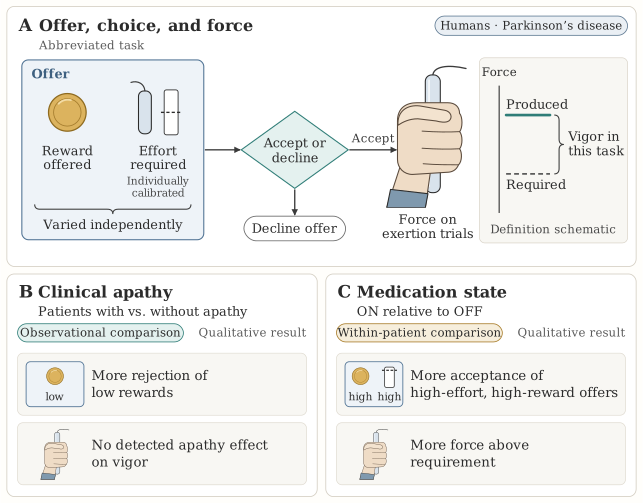
A study of 39 patients with Parkinson’s disease and 32 comparison participants separated choice from exertion. Offers independently varied monetary reward and the required handgrip force, calibrated to each participant’s capacity. Patients were tested ON and OFF their usual dopaminergic medication. Apathy was associated particularly with rejection of low-reward offers. Medication mainly increased acceptance of high-effort, high-reward offers and increased force above the required level on accepted trials—the study’s measure of vigor. Apathy did not have that same vigor effect [@leheronetal2018effort]. The clinical apathy comparison was observational; the ON/OFF comparison manipulated medication state. These findings do not identify one depleted transmitter as the cause of apathy.
The distinction becomes clearer when each contribution is paired with an observation.
| Contribution | Question for behavior | What the observation does not establish by itself |
|---|---|---|
| Reward sensitivity | How much does changing the expected reward change responding? | Pleasure, conscious desire, or willingness to pay every kind of cost |
| Effort acceptance | Which reward–effort offers are accepted? | A pure effort signal: reward, fatigue, ability, and alternatives also affect acceptance |
| Vigor | How fast or forcefully is the action performed under the task’s conditions? | Whether the person will start independently outside the task |
| Initiation | Does an action begin, and with what latency and dependence on prompting? | Whether the larger course will continue |
| Persistence | Does behavior continue as costs, delays, and evidence of progress change? | Whether continuing remains appropriate |
| Reinitiation | Does the person resume the relevant course after an interruption? | Intact maintenance merely because the goal can still be described |
These contributions interact throughout behavior. A first step toward the corridor changes posture, effort, and the visible route. That evidence can strengthen commitment or reveal a reason to stop. A reminder can change both the priority of the walk and the next movement. Expected effort already participates in valuation; it is not a toll assessed only after value has been computed. Nor must bodily preparation wait until a final choice is complete.
The same caution applies to wanting. A person can report wanting an outcome while doing little to obtain it. Another can work vigorously through a learned routine without experiencing a strong conscious desire. A cue can release an action whose value was already established. A medication can change vigor without correcting every aspect of apathy. There is no single quantity called wanting that is poured into an action until movement begins.
This decomposition also connects the chapter to Chapter 38. Initiation and maintenance are different control problems. One patient may begin repeatedly but abandon each course. Another may fail to start yet continue effectively once externally launched. A third may complete overlearned routines but not construct a new sequence. The apparent unity of motivation dissolves into dissociable operations.
42.5 A distributed initiation system
The overview’s anatomical framework (Section 36.3; Section 36.5; Section 36.6) supplies the setting for these dissociations. Severe reductions in spontaneous action can follow injury at several cortical and subcortical sites. We need to ask which relationships each lesion interrupts, while recognizing that one lesion can change several contributions at once.
42.5.1 Medial frontal systems relate goals to control and action
The medial frontal wall contains differentiated association and motor territories. Anterior cingulate and anterior midcingulate labels are not interchangeable; as Section 36.3 explained, some territory called dorsal anterior cingulate in functional studies is called anterior midcingulate in other anatomical schemes. Pre-SMA, SMA proper, and cingulate motor areas also have different connections. They should not be merged into one region for initiative.
The cortical routes make the functional question concrete. Macaque tracing distinguishes strong prefrontal input to rostral area F6, or pre-SMA, from the stronger primary-motor relationships of caudal F3, or SMA proper. Selected prefrontal territories also connect with cingulate motor areas [@luppino1993sma; @batesgoldmanrakic1993]. These routes allow contextual conditions to influence motor organization through differentiated partners. They establish connections, not a mandatory serial chain from thought through pre-SMA to movement.
Clinical lesions provide complementary evidence. Németh and colleagues described three patients with akinetic mutism whose common damage involved both rostral anterior cingulate gyri and neighboring supplementary-motor territory; other damage differed across cases [@nemethetal1988akinetic]. The shared injury implicates this medial frontal region and its connections, but it does not isolate one cortical field or establish which component of initiation failed.
Electrical stimulation supplies a different kind of evidence. In two patients undergoing epilepsy monitoring, stimulation of anterior midcingulate sites elicited bodily sensations, autonomic changes, and reports of approaching challenge accompanied by determination to meet it. Resting-state fMRI placed the sites in a wider functional network [@parvizi2013persevere]. The experiment altered a complex experienced state; it did not measure sustained performance on a perseverance task. Stimulation can also recruit connected tissue, and functional coupling does not identify direct axonal projections. The finding supports an interaction among bodily state, anticipated demand, and readiness, with those limits intact.
42.5.2 Basal ganglia, dopamine, and thalamus alter access to action
Basal-ganglia circuits influence which cortical and brainstem controllers gain access to action, how strongly learned consequences bias that competition, and how vigorously selected actions are expressed. Damage to caudate, putamen, globus pallidus, or their connections can therefore reduce spontaneous behavior even when elementary movement remains possible. The classic auto-activation cases make this especially clear [@laplaneetal1984psychic].
The output anatomy requires precision. In the dorsal basal-ganglia circuit, GPi and substantia nigra pars reticulata (SNr) are major inhibitory output nuclei. GPe, the external globus pallidus, participates extensively in internal and recurrent circuitry; it is not interchangeable with GPi. Ventral pallidum has a distinct place in ventral circuits. The overview traces these relationships and their thalamic and subcortical targets (Section 36.5; Section 36.6).
A loss of pallidal neurons cannot be interpreted as simply taking a brake off all movement. Effects depend on the territory, surviving pathways, and altered activity across the network. The pallidal case concerns mainly GPi, whereas other clinical reports support only broader basal-ganglia localization. Dopamine acts in surviving cortical and subcortical systems; a systemic drug response does not reveal its decisive site of action [@adametal2013dopamine].
Thalamus participates in continuing interaction rather than merely passing a completed decision back to cortex. Macaque tracing shows reciprocal and nonreciprocal relationships linking mediodorsal and ventral anterior/ventral lateral thalamic territories with frontal cortex [@mcfarlandhaber2002]. Clinical reports of markedly reduced self-generated behavior after thalamic injury are consistent with this distributed setting [@laplanedubois2001autoactivation; @darbyetal2018volition]. They do not, by themselves, assign the deficit to one nucleus, one disrupted projection, or one psychological operation.
42.5.3 A prepared organism must be available
An initiated course requires an organism able to perform it. A walk depends on wakefulness, posture, movement, and physiological support for exertion. Section 36.6 traced selected frontal routes to hypothalamic and brainstem regulation; Chapter 39 examined anticipatory preparation and returning bodily information. These processes can influence whether action begins and how long it continues. This does not require a new measurable autonomic response before every small action.
Brainstem lesions occur among the cases assembled by Darby and colleagues [@darbyetal2018volition], but their location alone does not establish that reduced arousal explains the behavior. Arousal, motor capacity, comprehension, and spontaneous initiation must be assessed separately. Raising arousal also need not restore appropriate goal-directed activity. Preparation has to remain related to context and the action being pursued.
{.callout-note #proposal-tomorrow-action-routes title=“Proposed figure 4 — Connections through which a 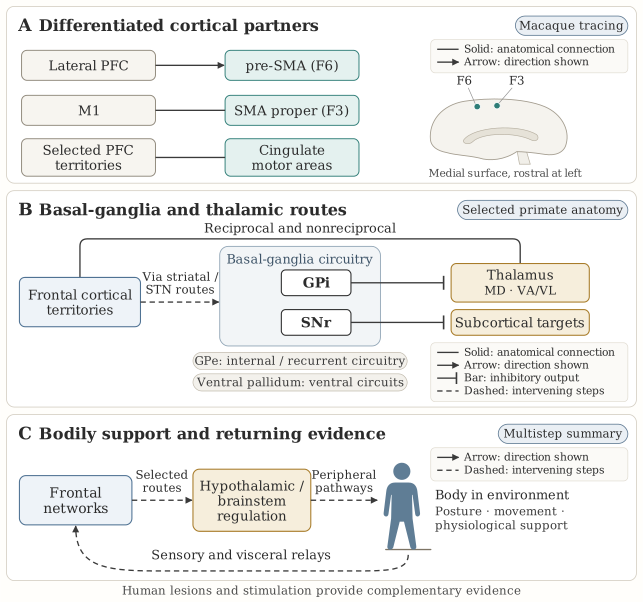
42.5.4 Different lesions can enter one network
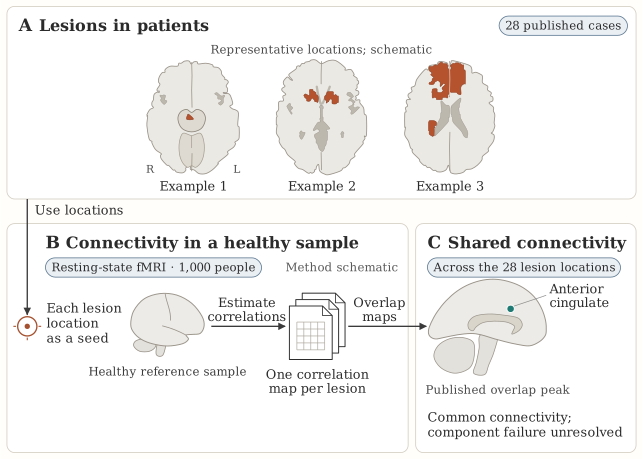
Darby and colleagues assembled 28 published cases in which focal lesions produced abulia or akinetic mutism. The lesions occurred at heterogeneous sites, including anterior cingulate cortex, pallidum, thalamus, caudate, and brainstem. They mapped each lesion location onto resting-state connectivity measured in a separate healthy sample. The locations shared functional connectivity with an anterior cingulate region [@darbyetal2018volition]. Thus the commonality was a relationship in a normative network, not overlap of every lesion within one anatomical center.
The result supports a network interpretation with important limits. The clinical reports differed in assessment and severity. Healthy-sample connectivity does not measure the surviving network in each injured patient or demonstrate that one particular connection failed in all of them. The analysis also cannot distinguish reduced reward sensitivity, impaired action organization, inadequate arousal, or several contributors acting together. Shared connectivity is not proof of a shared psychological subtraction.
The distributed account can now be stated precisely:
Initiation depends on interactions among the systems that represent a goal, evaluate its consequences and costs, organize movement, and support the body performing it. Similar inactivity can arise when different relationships fail.
42.6 The lobotomy record: historically important, anatomically uncontrolled
The title of this chapter came from lobotomy reports, but those reports require unusual care. The operations were destructive, the patients were heterogeneous, and the clinicians who promoted the procedures often judged their own results. The record is historically important. It is not a selective lesion experiment.
42.6.1 Several operations became one name
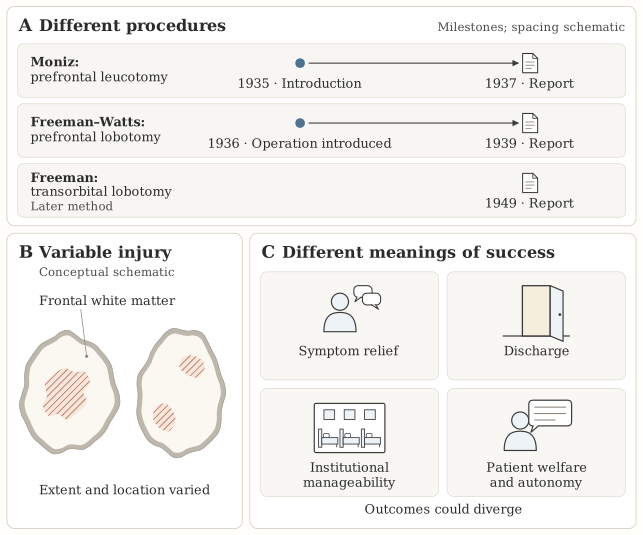
Egas Moniz introduced prefrontal leucotomy in Portugal in 1935 and published an English-language account in 1937. The procedure disrupted frontal white matter through openings in the skull. Moniz presented it as a treatment for severe mental disorders and claimed a degree of safety and effectiveness that later evidence did not justify [@moniz1937leucotomy].
Walter Freeman and neurosurgeon James Watts introduced their own prefrontal operation in the United States in 1936. Their standard prefrontal lobotomy used a different instrument and plane of section. It was this earlier operation—not the later transorbital method—that produced the 48 cases discussed in their 1939 paper on frontal-lobe function [@freemanwatts1939frontal].
Freeman subsequently promoted transorbital lobotomy, with an instrument entering through the orbital roof. His 1949 report described this later procedure [@freeman1949transorbital]. The route of entry must not be mistaken for selective damage to orbital or ventromedial cortex: it was intended to cut frontal white matter. Subsequent anatomical work examined the resulting lesions [@freemanwilliams1951lesions]. Changing techniques and variable damage make lobotomy an inadequate anatomical description on its own.
42.6.2 Treatment, discharge, and manageability were entangled
The operations spread through a psychiatric system with severely ill patients, overcrowded hospitals, limited staffing, and few treatments that reliably altered chronic psychosis, severe mood disorder, or relentless agitation. Surgeons and psychiatrists did not describe only one goal. They claimed relief of distressing symptoms, reduced agitation, discharge from hospital, restored family life, and return to employment. Institutional manageability was also an explicit and powerful outcome.
Those goals could conflict. A quieter ward was not necessarily evidence that a patient had recovered. Discharge could reflect family resources and postoperative supervision as much as symptom change. Employment was often treated as a sign of success, embedding expectations about productivity and social conformity in what appeared to be a medical outcome [@pressman1998lastresort; @raz2010psychosurgery]. Institutionalized people and patients dependent on family decisions were especially vulnerable to judgments made by physicians, administrators, and relatives rather than by the patients themselves.
Freeman’s own later follow-up of 3,000 patients illustrates the problem. He compared prefrontal and transorbital procedures, private and state-hospital patients, and diagnostic groups [@freeman1957followup]. These were observational comparisons in the promoter’s own follow-up record. Differences among groups cannot isolate a procedure’s benefit from case selection, illness history, living circumstances, and support after surgery.
42.6.3 Outcomes were heterogeneous
Some patients were described as less tormented, less agitated, or able to leave an institution. Others remained severely ill, relapsed, or underwent additional operations. Reported adverse outcomes included seizures, hemorrhage, infection, cognitive impairment, reduced initiative, emotional blunting, disinhibition, socially inappropriate behavior, personality change, and death. Contemporary controlled comparisons already noted uncertainty about surgical plane, lesion extent, therapeutic specificity, and the emotional and intellectual deficits produced [@pressman1998lastresort; @simonetal1951controlled].
The fact that some patients or families reported improvement does not rescue the practice. The procedures were generalized far beyond the quality of the evidence. Consent was often inadequate or coercive. Anatomical damage was irreversible and poorly controlled. Benefits were judged through standards that sometimes privileged institutional quiet, employability, or family convenience over the person’s autonomy and subjective life. Tens of thousands of lobotomies and related psychosurgical operations were performed in the United States during roughly two decades [@pressman1998lastresort].
The ethical conclusion does not require a cartoon in which every practitioner sought only placidity or every patient had the same outcome. The documented history is severe enough: crude destructive surgery was promoted rapidly, evaluated inadequately, and applied to people whose power to refuse was often limited.
42.6.4 A perceptive hypothesis from an uncontrolled record
Freeman and Watts nevertheless noticed something worth preserving. In their 1939 series, they described patients who could complete a task but did not reliably proceed to the next, appeared less troubled by error or failure, and discussed plans that did not govern later behavior. They summarized one recurring impression with the phrase “tomorrow never comes” [@freemanwatts1939frontal].
They proposed that frontal cortex contributes to the “projection of the whole individual into the future”: using past experience, anticipated consequences, and emotional significance to organize action before the outcome arrives [@freemanwatts1939frontal, pp. 536–537]. The formulation was remarkably prospective for 1939. It also bundled together several operations that the rest of this unit has worked to separate—representation, valuation, bodily anticipation, rule application, inhibition, initiation, and persistence.
The historical observation can therefore motivate a modern control problem. It cannot establish that lobotomy selectively removed future representation. The patients had different diagnoses before surgery, different lesions afterward, and variable changes in cognition, affect, social behavior, and movement. There was no matched control group capable of isolating one function. Even the apparent loss of initiative coexisted in some patients with impulsive or disinhibited acts.
The appropriate conclusion is narrower and stronger:
Extensive frontal white-matter injury can disrupt the ability of anticipated consequences and extended goals to organize behavior. The lobotomy record cannot tell us which component failed, where that component was located, or whether the same failure occurred in every patient.
42.7 The patient who could judge afterward
One patient in the Freeman and Watts report makes a narrower dissociation especially vivid. After surgery, he slapped nurses and pulled a fire alarm. When questioned afterward, he could recognize that the acts had been inappropriate. His difficulty, he said, was that “beforehand I couldn’t say whether or not it would be alright” [@freemanwatts1939frontal, pp. 536–537].
The statement contrasts retrospective evaluation with prospective control. Once the act and its social consequences were real, the patient could discuss them. Before acting, the same information did not constrain behavior effectively.
That observation does not reveal why. The patient may have failed to construct the likely consequence, assign it enough value, recruit an anticipatory bodily response, apply a social rule at the relevant moment, inhibit a prepotent action, or keep the consequence effective while action competition unfolded. Extensive frontal disconnection could disturb several of these operations at once.
The case belongs beside the distinctions between knowledge and effective control in Chapter 39 and The Futures of Others. It does not prove the somatic-marker hypothesis: no physiological signal was measured. Nor can the report determine whether the retrospective explanation accurately describes the information available before acting. It establishes a reported contrast between later judgment and earlier conduct, while leaving the mechanism unresolved.
The behavior also warns against merging lobotomy effects with abulia. Abulia produces too little spontaneous action. This patient produced actions that were excessive, poorly constrained, and socially inappropriate. A common framework is possible, but the shared failure lies at the level of extended control. In one case, an available goal fails to initiate action. In another, represented consequences fail to restrain it. They are not the same syndrome.
42.8 What “tomorrow never comes” can mean
The phrase should now be heard differently from the way the original lesion story invited us to hear it. It does not mean that an entire future has disappeared from the brain. A patient may still understand calendars, describe plans, remember obligations, or imagine an outcome. The phrase names a failure of transfer: what is represented does not acquire enough control over present behavior.
The clinical and experimental evidence gives the metaphor several meanings. Reward can have too little influence on responding. An acceptable outcome may not recruit the necessary effort. An instruction can be understood without specifying an effective starting action. A sequence can begin but fail to survive distraction, or can remain verbally available without resuming after a pause. These are distinguishable possibilities, not claims that every case preserves every other capacity.
Consider again the patient who agrees to walk. A specific prompt may support standing and the first step. The visible corridor then supplies evidence about progress; exertion changes the body and the cost of continuing. An interruption can require renewed organization of the same goal. Continued prompting might sustain the sequence, while a better-matched cue might allow more independent behavior. This is an explanatory example of the interacting control problems, not a claim that one prompting protocol works for every syndrome.
The organizing claim of Section 36.1 now has a clinical edge. A representation acts as a control state when it changes the use of other information or the recruitment of action. Being able to describe a plan demonstrates access to some of its content. It does not establish that the plan continues to organize behavior in a less structured situation.
I take these dissociations as evidence for the distributed work of initiative. They let us replace an undifferentiated lack of will with questions about what is preserved, what changes with context, and which intervention changes behavior. They do not turn those contributions into independent modules or prove a complete theory from one syndrome.
The language used for the patient also matters. A person does not become more or less “there” according to how much spontaneous behavior remains. Injury can alter initiative, emotional responsiveness, insight, language, memory, or movement while the patient remains a person whose welfare and preferences matter. The ethical failure of the lobotomy era included treating reduced disturbance or increased manageability as though it exhausted that question.
Frontal systems participate through the differentiated incoming, recurrent, and outgoing routes established in the overview. They remain dependent on sensory evidence, memory, bodily state, subcortical action systems, and feedback. The older regulatory machinery has not been replaced by a frontal executive. It is part of the machinery through which remembered and possible conditions become effective.
“Tomorrow never comes” is a clinical metaphor for a future that can remain cognitively available while failing to become behaviorally effective.
The metaphor accommodates failures of initiation without assuming that all other cognition is intact. It also accommodates poorly constrained action without calling disinhibition the same syndrome as abulia. In each case, the explanatory task is to identify how information fails to organize ongoing behavior.
42.9 Coda: constructing a future from remembered structure
This unit has asked how information beyond the immediate scene becomes effective in present control. A Common Currency examined comparison among outcomes whose significance depends on an organism’s state. Holding the Line examined continued influence across delay and interference. Feeling the Future examined prospective bodily preparation and returning bodily evidence. The Futures of Others examined how other agents’ knowledge, intentions, and outcomes enter control. Wandering When Full examined the allocation of information gathering. This chapter has separated contributions to starting, sustaining, and resuming action.
These are interacting problems. A bodily change can alter value during a maintained plan. New information can justify stopping a vigorous action. Another person’s expected response can change what is worth beginning. The chapter order is an order of explanation, not the order in which a brain completes a decision.
A complementary problem remains: where do the routes, scenes, relations, and events used in such control come from? Their construction is already part of the interactions we have described. Unit 7 will examine that contribution more closely. The nervous system does not create possible situations from nothing, and it need not construct a detailed imagined scene for every goal-directed act.
Episodic memory supplies details of particular experiences. In Hassabis and colleagues’ study, four of five patients with bilateral hippocampal damage were impaired in constructing novel imagined experiences, often producing fragments without a coherent spatial setting; one patient was relatively spared [@hassabis2007imagine]. This task concerns constructing experiences, not the ability to anticipate any consequence whatsoever. Addis and colleagues’ imaging study found overlapping as well as distinct activity while participants remembered past events and imagined future events, with the pattern depending partly on construction versus elaboration [@addisetal2007remembering]. Neither result makes remembering and imagining identical.
Semantic knowledge supplies facts and regularities that need not be retrieved as episodes. Spatial and relational knowledge constrains where events can occur; bodily state and current goals help determine which possibilities deserve elaboration. The constructive episodic simulation account proposes that flexible retrieval and recombination support imagining possible events [@schacteretal2007prospective]. It is a theoretical account, not evidence that all memory evolved for imagination or that prospective control always depends on an explicit episodic simulation.
The transition to Unit 7 changes explanatory focus within this same distributed organism. Maps and memories contribute to the possibilities that frontal and connected systems help make effective, while ongoing goals and action change what is learned and retrieved.
Unit 6 has asked how absent outcomes acquire control over present behavior. Unit 7 turns to the predictive maps and memories from which routes, scenes, events, and possible futures are assembled.
Established findings. Clinical reports distinguish spontaneous behavior from performance supported by external structure, with varying preservation of other capacities. In particular experiments, reward-dependent responding, effort acceptance, and force production have different relationships to clinical apathy and medication state. Lesions associated with severe reductions in spontaneous speech and movement are anatomically heterogeneous and can share normative functional connectivity. Historical lobotomy reports involved different procedures, patients, and outcomes; they are not selective experiments on future representation.
Working synthesis. A possible action may be described and potentially valued while exerting little influence on present behavior. Initiative depends on interactions among representation, valuation, action organization, bodily support, and feedback. This interpretation extends the unit’s embodied control account without positing a reservoir of will or making the six chapter problems into serial stages.
Open questions. Which measurements best distinguish reduced reward sensitivity, altered effort acceptance, impaired action organization, inadequate arousal, and deficient reinitiation in an individual? Why does a prompt help one person and fail another? How do dopaminergic and other systems interact across these patterns? How do the remembered and inferred situations examined in Unit 7 gain enough influence to begin, sustain, or appropriately change a course of action?